
Looking into the controversy over Ritalin and related drugs for controlling ADHD I was struck by a puzzle. Currently, about twelve percent of children are diagnosed with ADHD; those so diagnosed are widely claimed to be unable to function in a classroom without medication. The number is twice what it was thirty years ago. Ritalin was first synthesized in 1944, approved for medical use in the US in 1957, began to be used to treat children with ADHD in the sixties.[1] Before that, in the 1950’s when I was in school, classrooms functioned, judging by results, at least as well as they do now. That raises an obvious puzzle to which I can see several possible solutions:
1. The rate of ADHD has drastically increased. While that is not impossible, there seems to be no plausible explanation for such an increase. The only clear evidence on causation is that ADHD is in part genetic.
2. ADHD is in large part a bogus problem, the view of many of the critics of Ritalin use. Teachers get parents to drug their kids because it’s less trouble than dealing with normal kids undrugged. This seems to contradict the anecdotal evidence from parents who report large improvements in their children’s behavior as a result of the drugs but that might mean that one percent of children really have the problem and the rest don’t.
3. What has changed is not the prevalence of ADHD but the environmental requirements on kids. The same child who is functional in many other environments may be a serious problem if he is required to sit still and be quiet for most of six or seven hours a day. The point was made by one mother who commented that it was odd that her child only seemed to have ADHD nine months of the year: He was fine, undrugged, during the summer. Eighty or ninety years ago schools had classrooms in which kids had to sit and be quiet but for fewer hours of the day, fewer weeks of the year.
4. Undiagnosed ADHD kids were a serious problem in the past; while we have largely solved that problem with drugs, other school problems have gotten worse, which is why, on net, things are no better now than then. That seems inconsistent with at least the stronger claims about just how much of a problem ADHD is in the classroom and how common it is but those claims may be exaggerated.
5. Schools have changed in ways that make teachers less able to deal with disruptive students. That might mean the abandonment of physical discipline, loss of the option to expel students, more of the decisions about how to run a classroom handed down from above instead of made by the teacher. It might mean a decline in teacher quality as more other professions open up to women. Whatever the cause, schools have changed: more administrators, lower test scores, much higher costs. Perhaps they have become worse at dealing with the sort of kids that get diagnosed with ADHD.
6. In the past many students, especially the sorts of student who now are likely to be diagnosed with ADHD, were either frequently truant or not enrolled at all. Elementary school enrollment has been close to 100 % for more than a century, as shown below, but high school enrollment only reached its present level about 1970. I have been unable to find data on 20th century truancy rates; official figures on truancy apparently do not exist and if any historians have published estimates I have not found them. I did find that in the 1950’s Average Daily Attendance (ADA) hovered consistently around 80% to 90% of the eligible student population. Some part of that must have been due to children missing class occasionally, excused or unexcused absences, but ADA was up to about 93% before the Pandemic so the lower rate earlier could be part of the explanation.
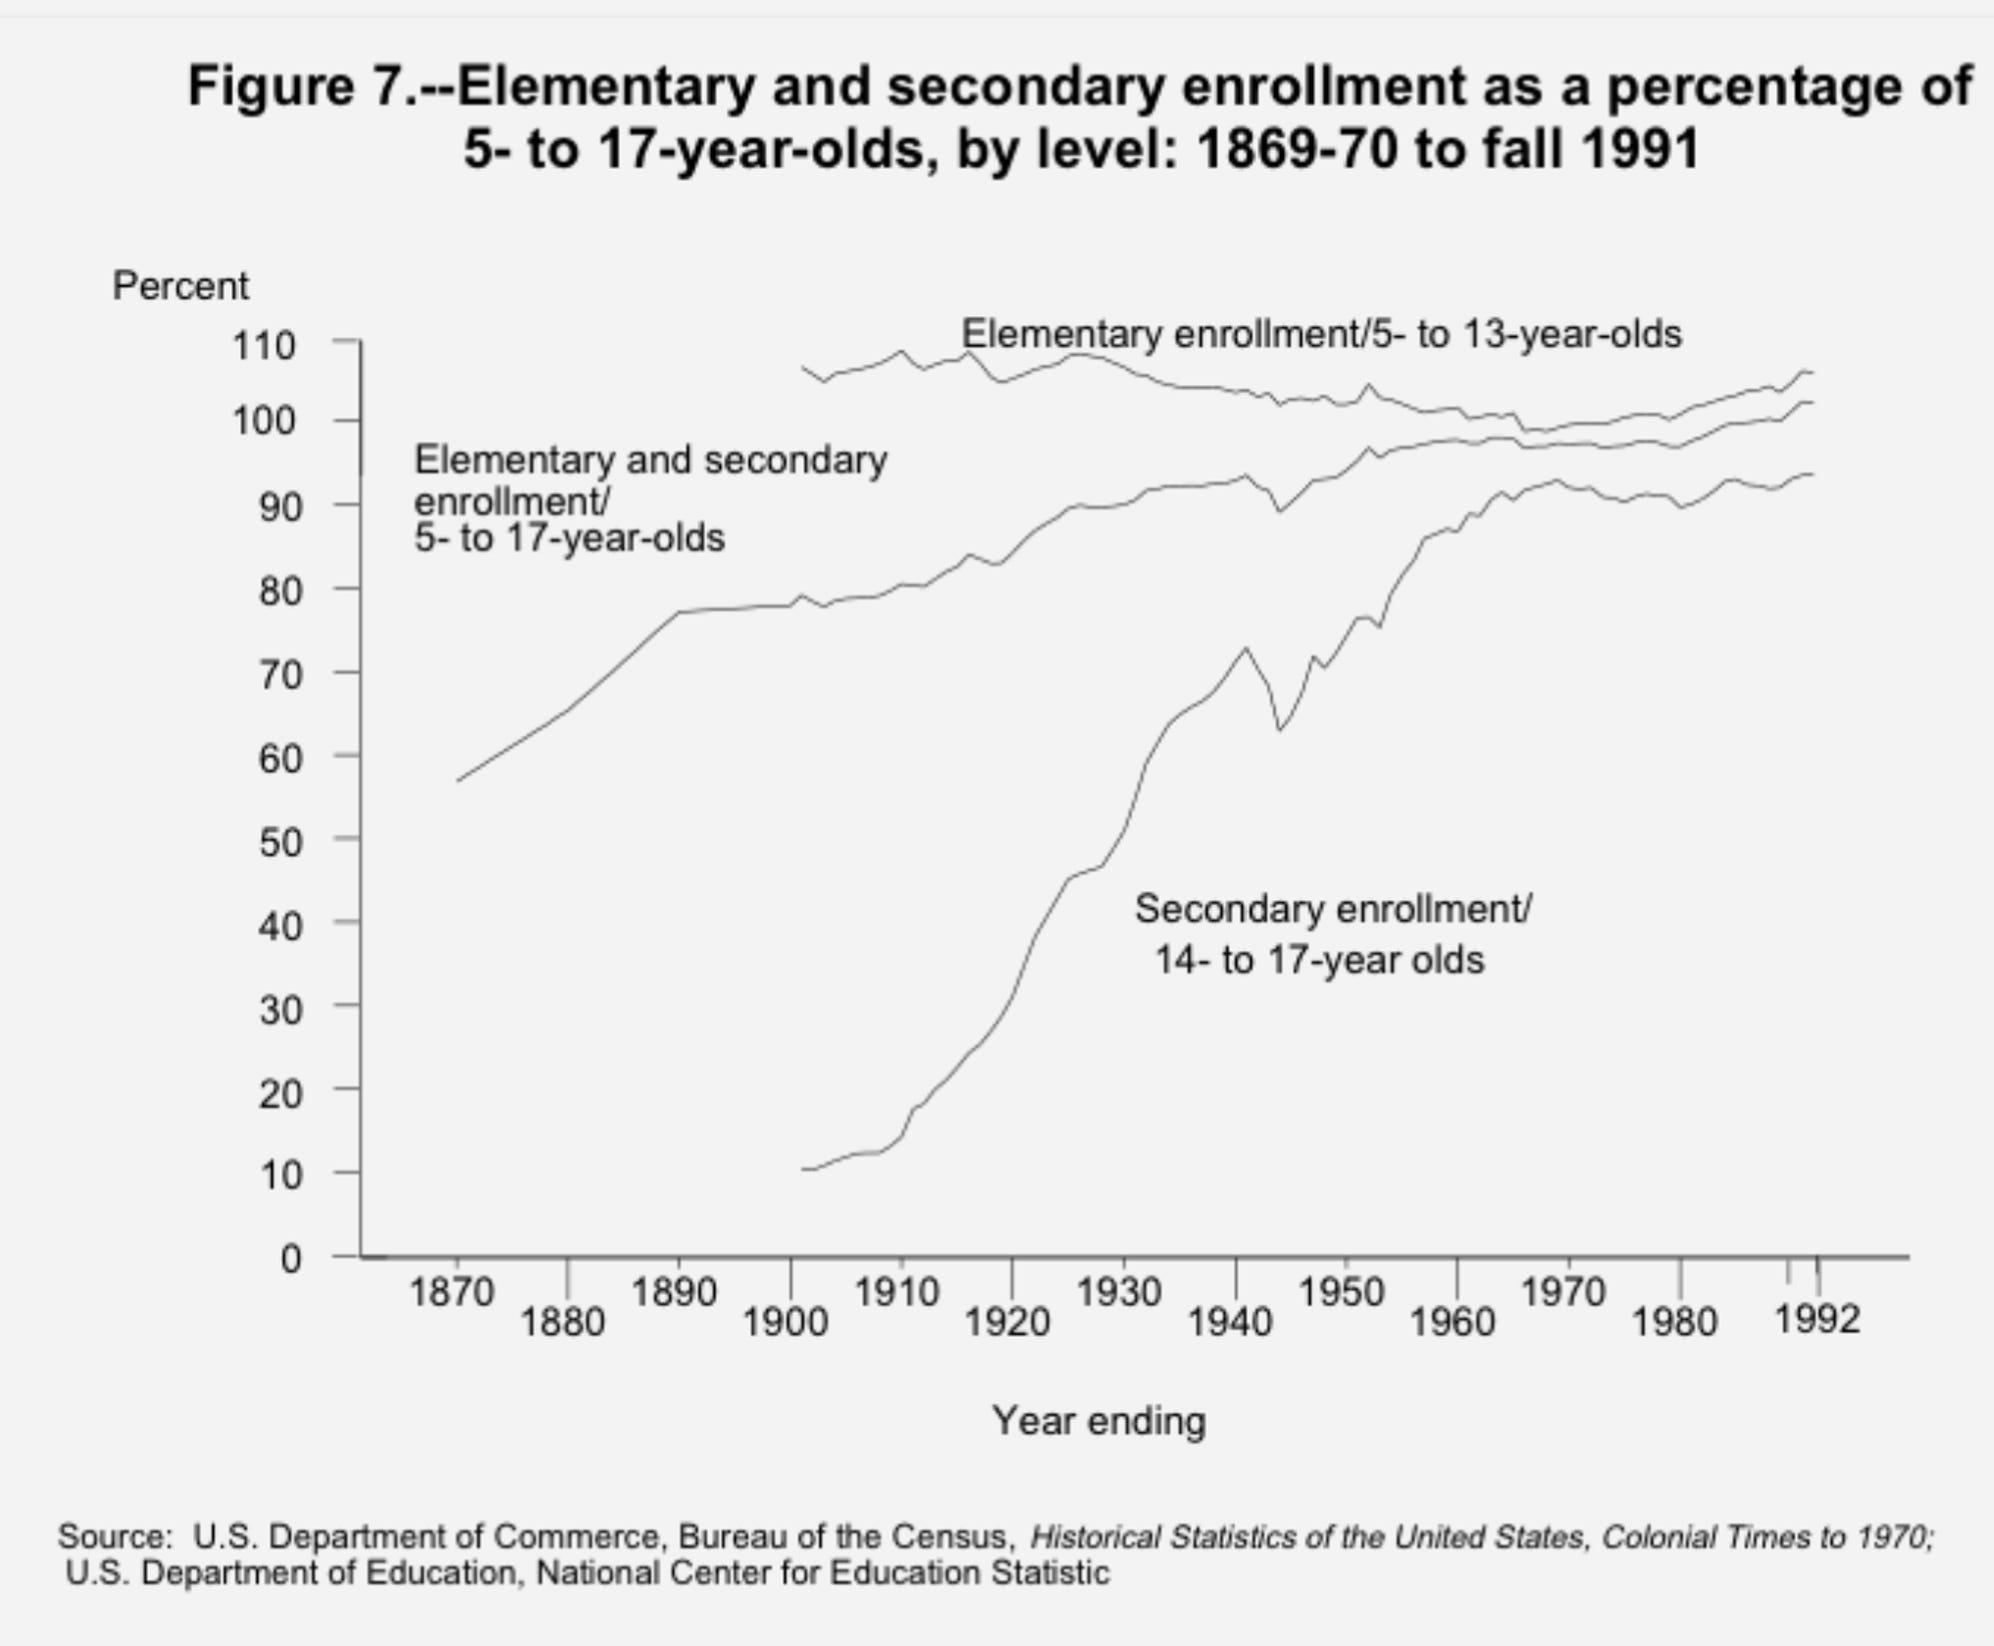
A teacher I put the puzzle to suggested an explanation that combines elements of several of these. In 1975 Congress passed legislation that required handicapped children to be included in the educational system and provided with accommodations to emulate as closely as possible the educational experience of other students. Prior to that, according to a congressional study, about 3% of school aged children were handicapped and receiving no education at all and about another 5% were receiving inadequate education.
Including what we now call “special needs” students in the school would explain some of the ADHD cases. The accommodations provided to them might make other students choose to claim special needs status, might also make teachers less able to impose classroom discipline. With looser classroom discipline levels of misbehavior that could have been controlled in the past might become uncontrollable.
As these comments suggest, I do not have a clear answer to the puzzle; very likely there are multiple causes. The effects of including handicapped students in the schools and making special provisions for them seems likely to be one.
My web page, with the full text of multiple books and articles and much else
Past posts, sorted by topic
A search bar for past posts and much of my other writing
A draft of my next book, Consequences of Climate Change, webbed for comments. Read it and tell me what I have wrong.
[1] Wiki. The scientific name is Methylphenidate. It has been sold under a number of trade names.
About a third of all high school students used to smoke. Nicotine has been shown to help with ADHD symptoms.
“…those so diagnosed are widely claimed to be unable to function in a classroom without medication.”
That, to me, is the crux of the issue. “Unable to function in a classroom” basically means: ‘unable to bend to their teacher’s will’. That’s not what a properly functioning mind does. It’s what a broken mind does.
Of course teachers will enroll doctors to drug kids to ‘help’ break their spirit.
To me, that quote reads as though someone had written about slaves in the 1850s: ‘…those diagnosed with drapetomania are widely claimed to be unable to function on the plantation without medication’. Drapetomania was a medical diagnosis at the time: slave life was viewed as so pleasant that only an insane person would want to flee. (I know it’s hard to believe but don’t take my word for it, look it up on Wikipedia.) Of course, there’s no such thing as a slave ‘functioning’ on the plantation. That’s a word only a slaveholder would use.
The first question any doctor should ask, in my opinion, before prescribing medication, is this is: **‘Is the patient free?’** If not, then free him first, and the need for medication may well go away.